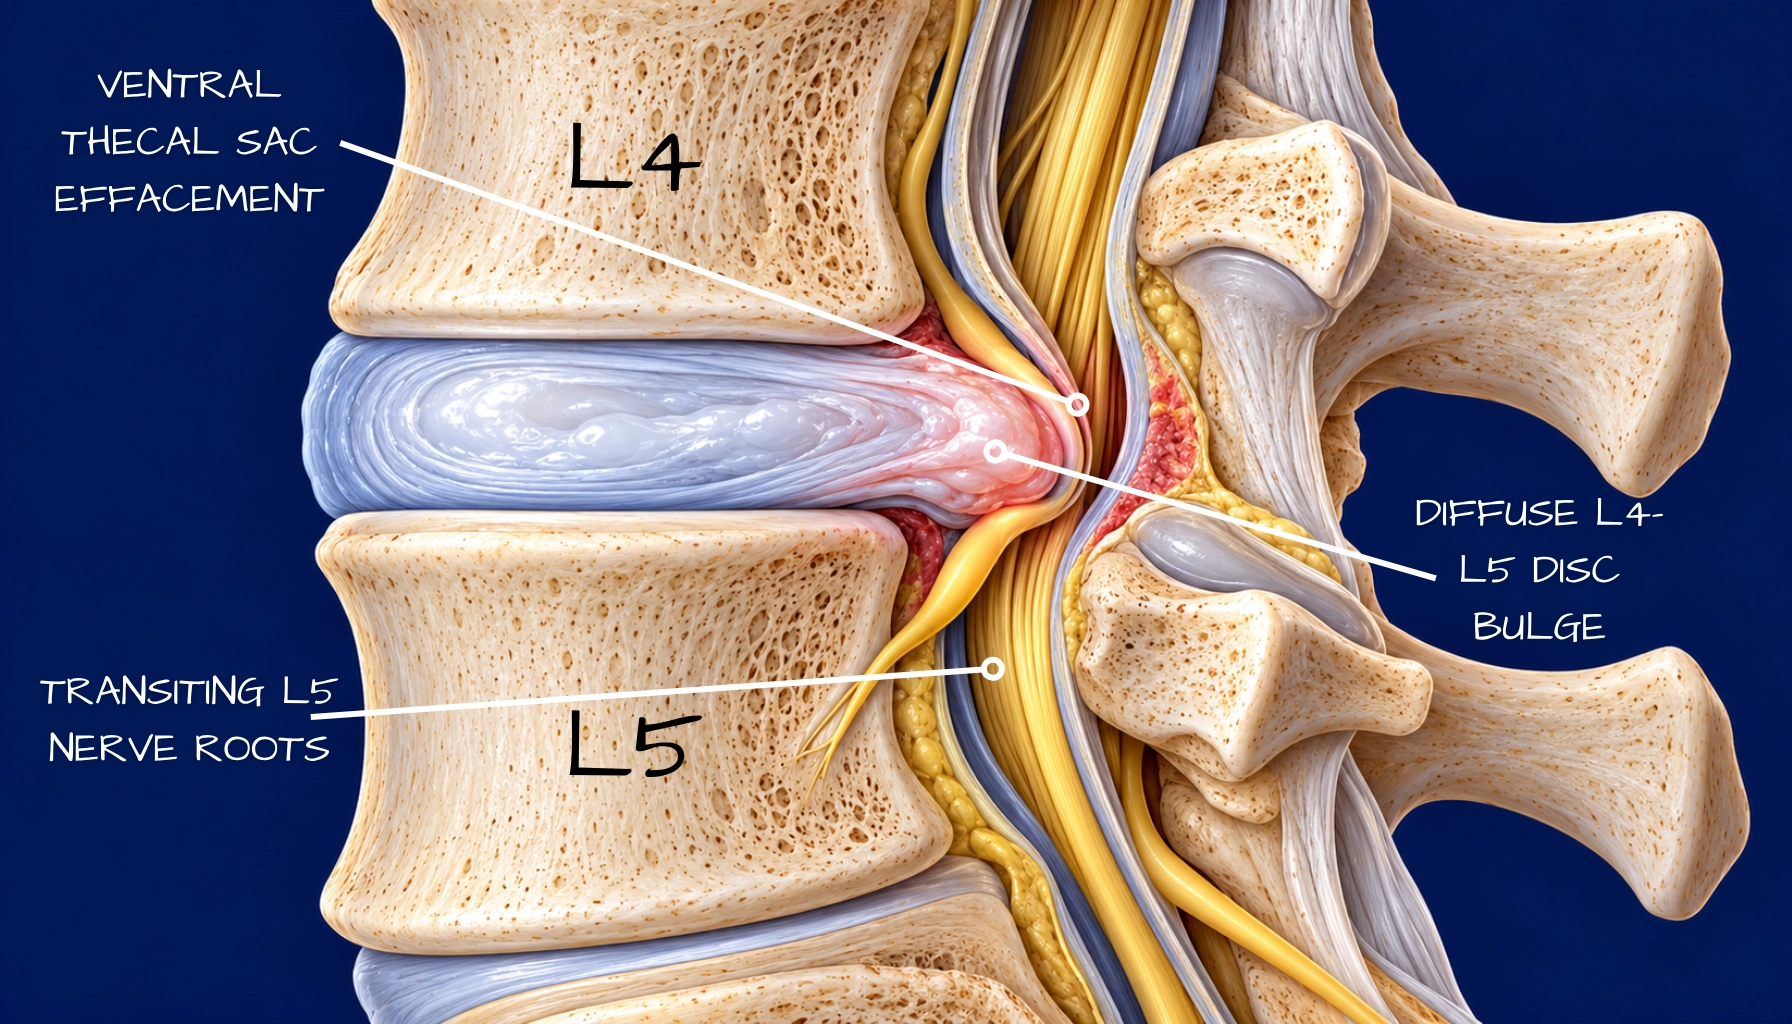
Slip disc is an everyday name rather than a diagnosis, and it can mean anything from a mild bulge to a fragment of disc lying free in the spinal canal.
Patients who have been told they have a slip disc usually ask me the same thing in the first minute, which is how serious it is. I cannot answer that from the term, because slip disc is the name people in India use for a whole range of findings, and some of them settle within weeks.
What a slip disc actually is
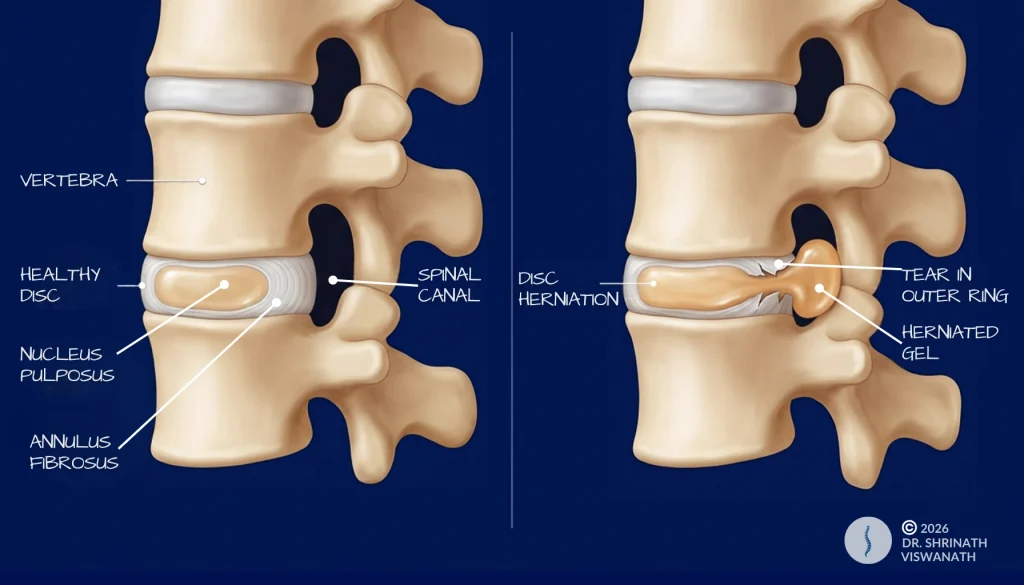
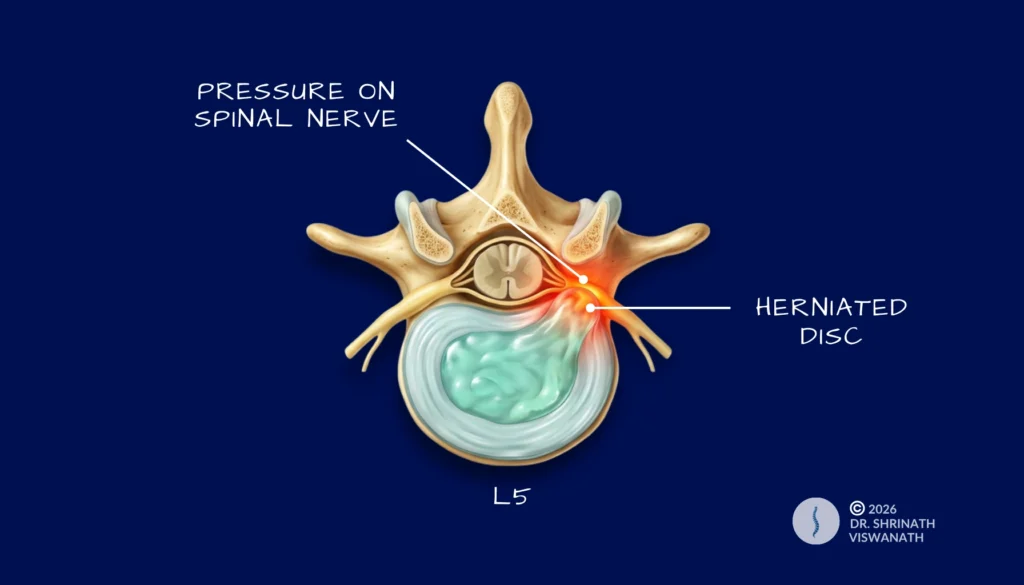
A disc is a cushion between two vertebrae, with a tough outer ring called the annulus fibrosus and a gel like centre called the nucleus pulposus. It cannot slip out of place as a whole. What happens is that the outer ring weakens or tears, and the gel pushes outward through the weak point. The tear usually builds up over years, and a single lift or twist is often just the moment it becomes noticeable.
The four stages of a slip disc
| Stage | What has happened | What it often feels like |
|---|---|---|
| Disc bulge | The disc extends evenly beyond its normal edge and the outer ring is intact | Often nothing, or mild back stiffness |
| Protrusion | Gel pushes into a tear in a small area of the outer ring | Back pain, and leg pain if the disc sits near a nerve root |
| Extrusion | Gel has pushed fully through the outer ring but is still connected to the disc | Leg pain, numbness or weakness are more likely |
| Sequestration | A fragment has broken away and lies free in the spinal canal | Often strong nerve symptoms, and the fragment can shift position |
When a slip disc presses on a nerve
Plenty of people with a herniation on their scan have no leg symptoms at all, and pain that stays in the back with no leg component makes nerve compression less likely. When disc material does press on a nerve root, the pain, numbness or tingling follows the path of that nerve down the leg, which is what people usually call sciatica. Larger herniations are often the ones that shrink. A systematic review of studies that followed disc herniations on repeat scans found spontaneous regression in 96% of sequestrations, 70% of extrusions, 41% of protrusions and 13% of bulges. The immune system is thought to clear the displaced gel over months, which is why a large fragment on the scan can still settle with time.
Signs that a nerve is involved
- Pain travelling down one leg
It usually runs from the buttock into the thigh, calf or foot on one side, following the path of the affected nerve.
- Numbness or tingling in the leg
You may feel it along the calf or the sole of the foot, and the area it covers tells me which nerve root is involved.
- Weakness when lifting the foot
Difficulty lifting the front of the foot as you walk, or pushing up onto your toes, points to weakness in the muscles that nerve supplies.
- Leg pain that eases on walking
Leg pain that is worse sitting or bending forward and eases when you walk or lie flat is a common pattern with a disc.
When to See a Doctor
Arrange a spine consultation if:
PLAN AN EVALUATION
- Leg pain, numbness or tingling has not improved after four to six weeks of regular exercise and pain relief
- You notice weakness in your foot or ankle, such as difficulty lifting the front of the foot
- Pain keeps you from sleeping or working
- Your scan shows an extrusion or sequestration and nobody has examined you to match it with your symptoms
- You have been told you have a disc herniation but have no clear plan for what happens next
SEEK URGENT CARE
- A sudden change in bladder or bowel function, such as difficulty passing urine or loss of control
- Numbness in the saddle area, meaning the inner thighs and around the anus
- Weakness or numbness in both legs that is getting worse quickly
These may be signs of cauda equina syndrome, a condition in which the nerve bundle at the base of the spinal cord is compressed. This requires same day orthopaedic or emergency evaluation. Do not wait.
COMMON QUESTIONS
Can massage or manipulation push a slip disc back in?
No. The gel has pushed through a tear in the outer ring, and nothing from outside can put it back. Physiotherapy helps by easing pain and keeping you moving, and I would be careful with forceful manipulation if you have leg pain or numbness.
Q2: Should I stay in bed until the pain settles?
No. A day or two of rest in a bad flare is reasonable, but longer tends to stiffen the back and slow recovery. Gentle walking within comfort is usually the better choice.
Q3: When does a slip disc need surgery?
Most people do not need it. It is considered when nerve symptoms keep getting worse or stay disabling after weeks of treatment, and the usual operation is a endoscopic discectomy or a micro-discectomy, which removes the part of the disc pressing on the nerve.
Q4: My scan shows a bulge but I have no pain. Should I worry?
No. Bulges are common on scans of people with no back pain, and a bulge on its own needs no treatment. My article on what a spine MRI report is telling you explains how to read the rest of your report.